Menopause and Trouble Sleeping: Strategies for Better Rest

Dr. Glenn J. Landry, PhD · Sleep and circadian rhythms scientist
Updated · 11 min read

The short version
Trouble sleeping in perimenopause and menopause is common, and it's real: in one survey cited by a 2018 review, 26% of perimenopausal women had insomnia severe enough to qualify for a diagnosis.[1]
Hot flashes are only part of it. Let's find what's actually waking you, work on what you do when you're awake, and talk to your physician about treatment. If you're reading this at 3 a.m., I get it.
Key takeaways
- Hot flashes can wake you, but not every time, so look for other causes too.[5][6]
- In one study, postmenopausal women had about 3.5 times the odds of moderate sleep apnea as premenopausal women. Ask your physician about snoring.[7]
- In one trial, CBT-I (a drug-free program) left 70% of women in the no-insomnia range at 8 weeks, versus 24% with menopause education.[11]
- A cool bedroom and light layers are about sleep comfort, not a hot flash treatment.[22][16]
Why does menopause bring trouble sleeping?
Maybe you've been told it's just stress, or just getting older. The research points somewhere more specific.
Perimenopause is the transition around your final period, from the first changes in your cycle to a year after it.
- In SWAN, a large US survey of 12,603 women aged 40 to 55, 38% reported difficulty sleeping in the past two weeks.[2]
- Menopausal stage was associated with sleep difficulty independent of other factors. Within this 40-to-55 age range, age on its own was not.[2]
A 2018 review adds that long-term studies link sleep difficulties with menopausal stage and with changes in estradiol and follicle-stimulating hormone, over and above the effects of age.[1]
Canadian data add a nuance. Among 6,179 women aged 45 to 60:
- Postmenopausal women more often reported taking 30 minutes or more to fall asleep (20.4% versus 15.5%).[3]
- They also more often met criteria for possible sleep-onset insomnia (10.8% versus 7.3%). Staying asleep did not differ.[3]
Here's the thing: it isn't the same for everyone. In a study that followed 255 women for up to 16 years, moderate-to-severe poor sleep was common (about 28% to 35% a year) but did not rise overall around the final period. Women who already had moderate-to-severe poor sleep beforehand had about 3.5 times the odds of it around menopause.[4] So if your sleep was already shaky, that's a good reason for us to work on it now.
Do hot flashes really wake you up?
Often, but not always. In a lab study of 34 perimenopausal women, 69% of 222 recorded hot flashes were associated with an awakening. Time awake linked to hot flashes averaged 16.6 minutes a night.[5] It was a small study, but it measured sleep and hot flashes directly.
Another lab study found something different. In women aged 46 to 51, screened for conditions such as sleep apnea and drug use, the researchers found no evidence that hot flashes produced sleep disturbance. Of awakenings within two minutes of a hot flash, 55.2% came before it and 40% after.[6] The authors suggested earlier findings may reflect disorders that were screened out of their sample.
A 2018 review puts it fairly: many, although not all, hot flashes are linked with awakenings.[1] So hot flashes at night, often called night sweats, deserve attention. But if we stop there, we may miss something else.
Could it be sleep apnea?
It's the one I'd hate for you to miss. Sleep apnea means repeated pauses or shallow stretches in breathing during sleep. In a Wisconsin study of 589 women, postmenopausal women had about 3.5 times the odds of 15 or more of these events an hour (moderate sleep apnea) as premenopausal women. That is after adjusting for age, body size and smoking. The margin of error was wide, and perimenopause showed no clear increase.[7]
In Canada, 14.6% of postmenopausal women screened positive for apnea, versus 10.4% of pre- and perimenopausal women.[3] And in a study published in 1997, an estimated 93% of women with moderate to severe sleep apnea had not been diagnosed at the time (among middle-aged employed adults in Wisconsin).[8]
These studies show links, not cause. Still, the Wisconsin authors recommended evaluation for sleep-disordered breathing for menopausal women who have snoring, daytime sleepiness or unsatisfactory sleep.[7] If that sounds like you (say, a partner has mentioned your snoring), talk to your physician. The good news: it can be checked.
What else could be waking you?
In a lab study of 102 women with disturbed sleep, recruited through newspaper ads, 53% had apnea, restless legs or both. Anxiety scores and hot flashes in the first half of the night were the best predictors of how well the women said they slept, though the link was modest.[9]
Alcohol is another, and the nightcap that helps you drop off is a classic example. In healthy volunteers, it shortened the time to fall asleep but increased sleep disruption in the second half of the night.[10] As I teach it, alcohol gives you "the perception that alcohol worked. I did fall asleep." The second half of the night pays for it.
Often more than one thing is going on. Here's a simple way we can sort the possibilities, together:
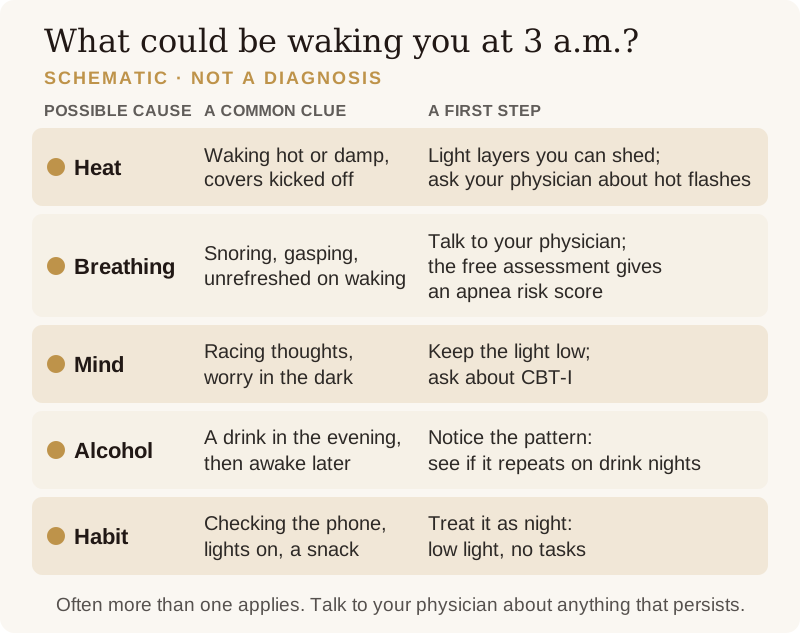
What actually helps menopause insomnia?
Let's start with the first-line option. For chronic insomnia, the first-line treatment is a skill, not a pill.[14] Cognitive behavioral therapy for insomnia (CBT-I) is a structured, drug-free program. In one trial it included sleep restriction, stimulus control, sleep hygiene education, cognitive restructuring and behavioral homework.[11]
That trial enrolled 106 peri- and postmenopausal women with insomnia symptoms and at least two hot flashes a day. After six phone sessions over eight weeks, 70% of the CBT-I group were in the no-insomnia range (84% at 24 weeks), versus 24% (43%) with menopause education. Hot flashes were no less frequent, but they interfered less.[11]
A second trial of 150 postmenopausal women with chronic insomnia found remission rates of 54% to 84% with CBT-I, versus 4% to 33% with sleep hygiene education alone.[12] CBT-I also improved fatigue, energy, sleepiness and work function.[13] In my experience, that fits: tips alone rarely fix it. Timing and behavior do.
The American College of Physicians recommends CBT-I as the first treatment for chronic insomnia disorder in adults.[14] Both trials above were single-site, so more research is welcome. Ask your physician how to reach a trained CBT-I provider. And you don't have to work out the rest alone.
What about hormone therapy, melatonin and sleep aids?
I'm a PhD, not an MD, so I won't tell you what to take. What I can do is walk you through what the medical societies and reviews say. After that, it's a conversation for you and your physician.
The Menopause Society (formerly NAMS) says hormone therapy remains the most effective treatment for hot flashes and night sweats; whether it suits you depends on your age, time since menopause and health history.[15] In a meta-analysis, hormone therapy improved sleep quality in women who had hot flashes, but not in women who did not.[17] The society also recommends several nonhormone options for hot flashes, including CBT and clinical hypnosis, but not supplements or herbal remedies.[16]
For melatonin, two meta-analyses of small randomized trials found no clear benefit for sleep quality in menopausal women, and both called for larger trials.[18][19] A 2021 analysis of 43 trials supported combined hormone therapy for sleep problems linked with hot flashes but found no significant effects of hypnotics.[20]
What I can tell you is my own position: I don't recommend melatonin or sleep medications as a fix. If you're using them, talk to your physician before changing anything. Hormone therapy is a medical decision for you and your physician.
How cool should your bedroom be?
You know the dance: covers on, covers off. Here's how I teach it. We tend to sleep best when we fall asleep after a peak in body temperature and then get a long, slow decline. Heavy bedding that traps heat can work against that. A very cold room has its own problem: when your core temperature reaches its lowest point, you can wake up cold and reaching for covers.
A review of heat and cold exposure found that, with bedding and clothing, heat increased wakefulness and reduced slow-wave and REM sleep. The review wasn't about menopause, and it stressed that bedding and clothing matter.[22] So I won't give you a magic number.

Be clear about the limit: a cool room is for sleep comfort. The Menopause Society lists cooling techniques among options it does not recommend for treating hot flashes, citing limited or inconsistent evidence.[16]
What should you do when you wake at 3 a.m.?
“It's what you do when you can't sleep that matters most.”
Let's make a plan for the next time you're awake at 3 a.m. In my teaching, light, activity and food are all daytime signals to your body clock. So I want you to keep the light low and the night quiet.
How do you make your days work for your nights?
It's not just what you do that matters, it's when you do it. Timing is everything. Your body clock relies on time cues: light most of all, plus activity and meals.
This is my coaching approach, not a finding from the menopause studies above. Here's what we'll work on together, as one piece of a plan with your physician:
Build the window and protect it, and your sleep accountant will balance the books. That's what I call the process that keeps track of the sleep your body needs.
Why does protecting your sleep matter for the long run?
Broken sleep can feel like a normal part of this stage of life. Here's the thing: just because it's normal doesn't mean it's healthy, and it doesn't mean it's inevitable.
I think in terms of what I call sleep health status: not just how you sleep tonight, but how you sleep across your whole lifespan. I'd argue that protecting it now is part of protecting your healthspan, your quality of life in later years. So let's treat these rough nights as something to work on, not something to put up with.
When should you get help?
Here's when I'd want you to see your physician: if you snore loudly, gasp, wake unrefreshed, feel tired all day, or feel low or anxious. Those are worth raising right away. And if poor sleep keeps going, don't wait it out. We're built to recover from a bout of poor sleep. It's when poor sleep becomes the pattern that it starts to cost you.
If you'd like company on this, we can help. Let's start with your own pattern. The Free Sleep Assessment includes a sleep apnea risk score (a screening score, not a diagnosis). Our Advanced Sleep Assessment reviews your wearable data with you. Your wearable can tell you what happened to your sleep last night. We tell you what to do about it, and what's worth bringing to your physician. We also have a page for women in perimenopause and menopause.
Where you start is entirely up to you. We meet you wherever you are on your journey.
Why does this matter at work?
For companies, menopause symptoms carry a cost too. In a Mayo Clinic survey (run in 2021, published in 2023) of 4,440 employed women aged 45 to 60, 13.4% reported at least one adverse work outcome due to menopause symptoms. The authors estimated US$1.8 billion a year in lost workdays in the US. That covers all menopause symptoms, not only sleep, and only 16.1% of invited women responded.[24] See sleep health for corporations.
Frequently asked questions
Does menopause cause insomnia?
Menopause is linked to it, though it isn't the only factor. Sleep difficulty is linked with menopausal stage, over and above the effects of age,[1] and Canadian data link menopause with more sleep-onset insomnia.[3] Poor sleep before menopause also predicts poor sleep around it.[4]
How long does menopause insomnia last?
Nobody can tell you for sure. The figure I can cite is for hot flashes and night sweats, not insomnia: frequent hot flashes and night sweats lasted a median of 7.4 years among women who had them, in one large US study.[23] Insomnia can be treated, though: in one trial of women with hot flashes, 70% of those given CBT-I were in the no-insomnia range at 8 weeks, versus 24% given menopause education.[11]
Why do I wake up at 3 a.m. in perimenopause?
There is no single reason. Hot flashes are one: 69% were associated with an awakening in one lab study.[5] Sleep apnea, a busy mind, evening alcohol and habits that treat the night like day are others.
What is the best sleep aid for menopause?
I'm a PhD, not an MD, so I can't recommend one. For chronic insomnia, the American College of Physicians puts CBT-I first.[14] Meta-analyses found no clear benefit of melatonin for sleep quality in menopausal women.[18][19] Talk to your physician about medicines and hormone therapy.
Can menopause cause sleep apnea?
Studies show a link, not a cause. In a Wisconsin study, postmenopausal women had about 3.5 times the odds of moderate sleep-disordered breathing as premenopausal women,[7] and more screened positive in a Canadian one.[3] If you snore or wake unrefreshed, talk to your physician or take the Free Sleep Assessment.
For perimenopause and menopause
See your own sleep pattern
Let's start with your own data. We'll help you see the pattern in your broken nights and what to change at home, and flag what's worth raising with your physician.

About the author
Dr. Glenn J. Landry, PhD
Sleep and circadian rhythms scientist · Founder, NEOS Performance
Dr. Glenn J. Landry, PhD, is a sleep and circadian rhythms scientist with 30 years in sleep science, and the founder of NEOS Performance in Delta, BC. He came to this field honestly: he couldn't sleep, starting at 13. He earned his PhD at Simon Fraser University and completed a postdoctoral fellowship at the University of British Columbia, studying sleep, aging and cognition. He created the Surviving Shift Work® program. Today Dr. Landry and the NEOS team guide executives, shift workers, first responders and organizations toward Elite Sleep®, translating science for each person's lived experience.
More about Dr. Landry Sources (24)
- [1] Baker FC, de Zambotti M, Colrain IM, Bei B. Sleep problems during the menopausal transition: prevalence, impact, and management challenges. Nature and Science of Sleep. 2018;10:73–95. (A review. The 26% comes from one 2006 phone survey of 982 California women, reported for perimenopausal women with a DSM-IV insomnia diagnosis.) Baker et al., 2018 (PubMed)
- [2] Kravitz HM, Ganz PA, Bromberger J, Powell LH, Sutton-Tyrrell K, Meyer PM. Sleep difficulty in women at midlife: a community survey of sleep and the menopausal transition. Menopause. 2003;10(1):19–28. (Self-reported sleep difficulty in the past 2 weeks; a survey, not a clinical measure.) Kravitz et al., 2003 (PubMed)
- [3] Zolfaghari S, Yao C, Thompson C, et al. Effects of menopause on sleep quality and sleep disorders: Canadian Longitudinal Study on Aging. Menopause. 2020;27(3):295–304. (Cross-sectional and self-reported.) Zolfaghari et al., 2020 (PubMed)
- [4] Freeman EW, Sammel MD, Gross SA, Pien GW. Poor sleep in relation to natural menopause: a population-based 14-year follow-up of midlife women. Menopause. 2015;22(7):719–726. (255 women followed up to 16 years; findings differ from other cohorts.) Freeman et al., 2015 (PubMed)
- [5] de Zambotti M, Colrain IM, Javitz HS, Baker FC. Magnitude of the impact of hot flashes on sleep in perimenopausal women. Fertility and Sterility. 2014;102(6):1708–1715. (Small sleep-lab study, 34 women.) de Zambotti et al., 2014 (PubMed)
- [6] Freedman RR, Roehrs TA. Lack of sleep disturbance from menopausal hot flashes. Fertility and Sterility. 2004;82(1):138–144. (Small controlled laboratory study.) Freedman & Roehrs, 2004 (PubMed)
- [7] Young T, Finn L, Austin D, Peterson A. Menopausal status and sleep-disordered breathing in the Wisconsin Sleep Cohort Study. American Journal of Respiratory and Critical Care Medicine. 2003;167(9):1181–1185. (589 women; wide confidence interval; odds ratio 3.5, 95% CI 1.4–8.8 for 15 or more events an hour.) Young et al., 2003 (PubMed)
- [8] Young T, Evans L, Finn L, Palta M. Estimation of the clinically diagnosed proportion of sleep apnea syndrome in middle-aged men and women. Sleep. 1997;20(9):705–706. (1997 data; 4,925 employed adults.) Young et al., 1997 (PubMed)
- [9] Freedman RR, Roehrs TA. Sleep disturbance in menopause. Menopause. 2007;14(5):826–829. (102 women with disturbed sleep, recruited through newspaper advertisements.) Freedman & Roehrs, 2007 (PubMed)
- [10] Ebrahim IO, Shapiro CM, Williams AJ, Fenwick PB. Alcohol and sleep I: effects on normal sleep. Alcoholism: Clinical and Experimental Research. 2013;37(4):539–549. (A review of studies in healthy volunteers, not specific to menopause.) Ebrahim et al., 2013 (PubMed)
- [11] McCurry SM, Guthrie KA, Morin CM, et al. Telephone-based cognitive behavioral therapy for insomnia in perimenopausal and postmenopausal women with vasomotor symptoms: a MsFLASH randomized clinical trial. JAMA Internal Medicine. 2016;176(7):913–920. (106 women; single-site trial; percentages are of the women assessed at each follow-up.) McCurry et al., 2016 (PubMed)
- [12] Drake CL, Kalmbach DA, Arnedt JT, et al. Treating chronic insomnia in postmenopausal women: a randomized clinical trial comparing cognitive-behavioral therapy for insomnia, sleep restriction therapy, and sleep hygiene education. Sleep. 2019;42(2):zsy217. (150 women; single-site trial; remission ranges cover the post-treatment and 6-month follow-ups.) Drake et al., 2019 (PubMed)
- [13] Kalmbach DA, Cheng P, Arnedt JT, et al. Improving daytime functioning, work performance, and quality of life in postmenopausal women with insomnia: comparing cognitive behavioral therapy for insomnia, sleep restriction therapy, and sleep hygiene education. Journal of Clinical Sleep Medicine. 2019;15(7):999–1010. Kalmbach et al., 2019 (PubMed)
- [14] Qaseem A, Kansagara D, Forciea MA, Cooke M, Denberg TD; Clinical Guidelines Committee of the American College of Physicians. Management of chronic insomnia disorder in adults: a clinical practice guideline from the American College of Physicians. Annals of Internal Medicine. 2016;165(2):125–133. (Strong recommendation, moderate-quality evidence; not specific to menopause.) Qaseem et al., 2016 (PubMed)
- [15] The 2022 hormone therapy position statement of The North American Menopause Society (now The Menopause Society). Menopause. 2022;29(7):767–794. The Menopause Society, 2022 (PubMed)
- [16] The 2023 nonhormone therapy position statement of The North American Menopause Society (now The Menopause Society). Menopause. 2023;30(6):573–590. (About treating hot flashes and night sweats, not sleep.) The Menopause Society, 2023 (PubMed)
- [17] Cintron D, Lipford M, Larrea-Mantilla L, et al. Efficacy of menopausal hormone therapy on sleep quality: systematic review and meta-analysis. Endocrine. 2017;55(3):702–711. (Trials at moderate to high risk of bias; heterogeneous studies limit certainty.) Cintron et al., 2017 (PubMed)
- [18] Yi M, Wang S, Wu T, et al. Effects of exogenous melatonin on sleep quality and menopausal symptoms in menopausal women: a systematic review and meta-analysis of randomized controlled trials. Menopause. 2021;28(6):717–725. (Sleep quality pooled from four trials; the authors call for larger trials.) Yi et al., 2021 (PubMed)
- [19] Du J, Tan Y. A systematic review and meta-analysis of randomized controlled trials investigated the effects of melatonin supplementation on bone mineral density, quality of life, and sleep in menopausal women. Frontiers in Nutrition. 2026;13:1687221. (No significant improvement in sleep quality; the authors call the evidence inconclusive and ask for large trials. Many of the trials combined melatonin with other ingredients, so the effect of melatonin alone is unclear.) Du & Tan, 2026 (PubMed)
- [20] Cheng YS, Tseng PT, Wu MK, et al. Pharmacologic and hormonal treatments for menopausal sleep disturbances: a network meta-analysis of 43 randomized controlled trials and 32,271 menopausal women. Sleep Medicine Reviews. 2021;57:101469. Cheng et al., 2021 (PubMed)
- [21] Watson NF, Badr MS, Belenky G, et al. Recommended amount of sleep for a healthy adult: a joint consensus statement of the American Academy of Sleep Medicine and Sleep Research Society. Journal of Clinical Sleep Medicine. 2015;11(6):591–592. (Applies to adults aged 18 to 60.) Watson et al., 2015 (journal)
- [22] Okamoto-Mizuno K, Mizuno K. Effects of thermal environment on sleep and circadian rhythm. Journal of Physiological Anthropology. 2012;31:14. (A review; not specific to menopause.) Okamoto-Mizuno & Mizuno, 2012 (PubMed)
- [23] Avis NE, Crawford SL, Greendale G, et al. Duration of menopausal vasomotor symptoms over the menopause transition. JAMA Internal Medicine. 2015;175(4):531–539. (SWAN, 1,449 women with frequent hot flashes or night sweats; observational. Measures hot flashes, not insomnia.) Avis et al., 2015 (PubMed)
- [24] Faubion SS, Enders F, Hedges MS, et al. Impact of menopause symptoms on women in the workplace. Mayo Clinic Proceedings. 2023;98(6):833–845. (Survey of 4,440 employed women aged 45–60 receiving primary care at Mayo Clinic sites; 16.1% response rate; 93% White; the US$1.8 billion figure is the authors' estimate from workdays missed.) Faubion et al., 2023 (PubMed)


