Sleep Health and First Responder Performance and Safety

Dr. Glenn J. Landry, PhD · Sleep and circadian rhythms scientist
Updated · 10 min read

The short version
Short and broken sleep is common in first responders, and it is linked to crashes, injuries, errors and burnout. In large North American studies, about 37% of firefighters and 40% of police officers screened positive for a sleep disorder, and most of the officers had never been diagnosed.[1][2]
That isn't weakness, and it isn't a lack of toughness. It's physiology, and the job works against it. The good news: in a randomized trial in one US fire department, sleep education plus screening cut disability days by almost half.[6]
Key takeaways
- About 37% of firefighters and 40% of police officers screened positive for a sleep disorder. A screen is not a diagnosis.[1][2]
- After 17 to 19 hours awake, performance on some tests is as poor as at a 0.05% blood alcohol level.[12]
- In one police department, injuries were 72% more frequent on the midnight shift than on days.[9]
- In one randomized trial, a sleep health program cut firefighter disability days by 46%.[6]
Why are first responders so short on sleep?
In this line of work, being tired is just part of the job. Everyone says so. Here's the thing: just because it's normal doesn't mean it's healthy, and it doesn't mean it's inevitable.
Look at what the job asks. Firefighters' schedules include extended shifts and long work weeks.[6] Calls break up the night. Rosters rotate. Overtime and court dates eat into recovery. And as I told a room of first responders in 2019, in a single day you can face more trauma than most of us do in a lifetime.
Add it up and the sleep window gets squeezed from every side. The body clock doesn't care about the roster, either. That's the key: it's not just how much responders sleep, it's when.
How common are sleep disorders in firefighters, police and paramedics?
More common than most people think:
- Firefighters: of 6,933 firefighters in 66 US departments, 37.2% screened positive for a sleep disorder. Sleep apnea was the most common (28.4%).[1]
- Police: of 4,957 officers in the US and Canada, 40.4% screened positive for at least one sleep disorder, most of them not previously diagnosed.[2]
- Paramedics and EMS: in a survey of 547 workers at 30 agencies, 55% were fatigued, and average sleep quality was in the poor range.[3]
- Medical first responders overall: across 28 studies, the pooled rate for each of shift work disorder, sleep apnea, insomnia and excessive daytime sleepiness was roughly 3 in 10. The ranges were wide.[4]
- Canada: of 5,813 public safety personnel in a self-selected online survey, 49 to 60% in each group reported symptoms consistent with clinical insomnia.[5]
"Screened positive" means a questionnaire flagged a possible problem. It isn't a diagnosis, and most of these surveys rely on self-report. I'm a PhD, not an MD, so if this sounds like you, that's a conversation for your doctor. The good news: a flag is information, and information is where change starts.
Is being awake 24 hours really like working drunk?
On some tests, performance is comparable. Not identical. After about 17 to 19 hours awake, transport workers and army personnel performed on some tests as poorly as, or worse than, they did at a 0.05% blood alcohol level.[12] After about 24 hours awake, a hand–eye coordination task matched roughly 0.08 to 0.10%.[13] By about 21 hours, some driving-simulator measures matched 0.08%.[14]
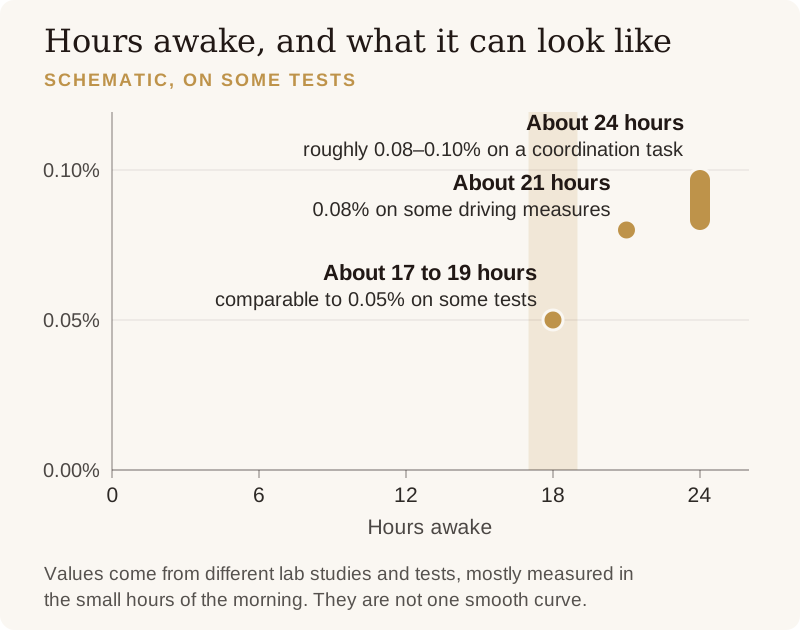
Here's what the headline leaves out. Most of those tests ran late at night or in the small hours of the morning, as the body clock heads toward its low point, so hours awake and time of day are mixed together.[12][13] Alcohol and sleep loss also hurt different skills: on the driving simulator, alcohol did more damage to speed control and staying on the road.[14] So think of it as a warning, not an exact equation. A tired driver is still an impaired driver.
Broken sleep counts too. In a lab study built to mimic firefighting, both a night with no sleep and a night broken by three 60-minute awakenings increased attention lapses and slowed task-switching.[15] The good news: a long shift is a risk you can see coming and plan for.
How does poor sleep affect safety on the job?
Each finding below comes from a different study, and most rely on self-report.
- Driving: firefighters who screened positive for a sleep disorder had about twice the odds of reporting a motor vehicle crash.[1]
- EMS: fatigued EMS workers had 1.9 times the odds of injury and 2.2 times the odds of a medical error or adverse event. The authors call it preliminary evidence.[3]
- Police on nights: in one mid-sized urban department, injuries were 72% more frequent on the midnight shift than on days.[9] Back-to-back night shifts carried about 4.3 times the odds of a public complaint, and about 4.7 times when court hours fell between them.[10]
- Five nights in a row: after five consecutive night shifts, 29 patrol officers did worse on simulated driving and vigilance than after three days off.[11]
Muscles may hold up better than minds. In simulated hot wildfire conditions, two nights with only a four-hour sleep opportunity did not change firefighters' physical task performance.[16] The clearer risks are to attention, mental flexibility and driving.[15][1]
That's the bad news. The good news: schedules and sleep habits can both change.
Why don't tired responders notice?
I hear it a lot: "Glenn, I can function really well on four or five hours." I'm sorry. You may feel like you're great, but you aren't your best self when you're sleep deprived.
There is science behind that. In a classic experiment, healthy adults limited to six hours or less in bed a night for two weeks performed as if they had missed up to two nights of sleep entirely. They were largely unaware of it.[17] Like someone who has had a few drinks, a tired person is a poor judge of whether they are fit to drive. And 26.1% of surveyed officers reported falling asleep at the wheel at least once a month.[2]
“It is a mistake for us in a fatigue risk management system to ask, are you fit for duty? Do you feel like you're okay? Because… you're not the best judge sometimes.”
There's another important point. You might feel fit for duty right now, but that says nothing about how you'll feel 90 minutes from now. Cognitive function rises and falls with our circadian rhythms across the day,[18] and one small early study even found shorter swings of roughly 60 to 100 minutes.[19] So the real question isn't 'Are you fit for duty right now?' It's 'Are you fit for duty now, and for the hours to come?' That's why a quick check at the start of a shift can't be the safety system. We need objective measures built into the work, and peer support around sleep, not a public confession at the start of a shift.
How is poor sleep linked to burnout and PTSD in first responders?
Sleep and mental health travel together. Among 6,307 North American firefighters, those who screened positive for insomnia had 3.78 times the odds of emotional exhaustion, a core sign of burnout.[20] Among Canadian public safety personnel, those who screened positive for insomnia were 3.4 to 7.0 times more likely to screen positive for a mental disorder.[5] A meta-analysis linked insomnia in medical first responders with depression, anxiety and PTSD.[4] These are associations. They can't tell us which comes first.
The prefrontal cortex is the CEO of the brain: reason, logic, decision-making. It's also the brake pedal. In a small study of people kept awake for a night, the amygdala, the brain's emotional center, reacted more strongly to upsetting images, and its link to that brake weakened.[21] Picture an officer who has just ended a chase, fully charged. That's when you need the brake. Officers who screened positive for a sleep disorder somewhat more often reported uncontrolled anger toward suspects (34% vs 29%).[2]
I said it plainly in 2019: "If we are going to address mental health, we must also address sleep at the same time." The good news is that sleep is something you can start on this week.
When are first responders most at risk?
It's not just what you do that matters, it's when you do it. Circadian rhythms are daily biological rhythms of physiology and behavior. We all have them. Alertness follows one, with two predictable dips: the overnight low, roughly 2 to 6 a.m., and the mid-afternoon lull.
Road-safety data show the pattern. Accident risk has a clear daily rhythm with a major peak around 3 a.m.,[22] and sleep-related crashes cluster in the early morning and again in mid-afternoon.[23] Responders drive in those hours, on calls and on the way home. In police data, injuries on the first day back on midnights were 69% more frequent than on days.[9]
The overnight low isn't a character flaw. It's physiology. We need to stop fighting our physiology and work with it. The core message of my Surviving Shift Work® program is to take the shift out of shift work: keep your body clock as close to a day schedule as the roster allows, rather than flipping it back and forth. For the night shift side of the story, read the best sleep schedule for night shift workers.
What can fire, police and EMS leaders do?
Now, let me be very clear. You cannot manage fatigue. The only way to manage fatigue is to get the sleep you need. What you can manage is the risk: find when your people are most exposed and put your effort there.
Every service is different, so start with a day in the life of your crew. The goal is the best sleep possible given the demands of the job.
How can first responders sleep better? What you can do this week

If you snore loudly, wake up gasping, or still feel exhausted with a steady sleep window, talk to your physician. How far you take any of this is entirely up to you. More: sleep support for first responders.
Frequently asked questions
Do firefighters sleep on 24-hour shifts?
Many get some sleep when calls allow, but alarms break it up. Broken sleep counts: a night split by three awakenings increased attention lapses in a lab study, as a night with no sleep did.[15]
How does sleep deprivation affect first responders?
Research links short and broken sleep to attention lapses, crashes, errors, injuries, burnout and PTSD symptoms. Most of it shows association, not proof of cause.[1][3][4][20]
Is being awake for 24 hours like being drunk?
Comparable on some tests, not identical. After 17 to 19 hours awake, performance on some tests matched or fell below that at 0.05% blood alcohol.[12] After about 24 hours, a coordination task matched roughly 0.08 to 0.10%.[13]
What can a department do about first responder fatigue?
Start with sleep education and voluntary screening: a randomized fire department trial saw 46% fewer disability days.[6] Add fatigue measurement, planned naps, shorter shifts where possible,[7] smarter rosters[10] and a fatigue risk management system (CSA Z1615 in Canada).[24]
How can first responders sleep better after a shift?
Protect a steady sleep window, keep the room dark, cool and quiet, and keep caffeine early. Nap before your first night shift, and on shift whenever it's safe and policy allows. Snoring, gasping or insomnia that won't budge? Talk to your physician, or take the Free Sleep Assessment.
For fire, police and EMS
Bring sleep science to your crew
Education comes first. NEOS Performance offers workshops, sleep health programs and the Surviving Shift Work® course that help responders understand why sleep matters, what gets in the way, and how to protect it, built around how your service actually runs.

About the author
Dr. Glenn J. Landry, PhD
Sleep and circadian rhythms scientist · Founder, NEOS Performance
Dr. Glenn J. Landry, PhD, is a sleep and circadian rhythms scientist with 30 years in sleep science, and the founder of NEOS Performance in Delta, BC. He came to this field honestly: he couldn't sleep, starting at 13. He earned his PhD at Simon Fraser University and completed a postdoctoral fellowship at the University of British Columbia, studying sleep, aging and cognition. He created the Surviving Shift Work® program. Today Dr. Landry and the NEOS team guide executives, shift workers, first responders and organizations toward Elite Sleep®, translating science for each person's lived experience.
More about Dr. Glenn J. Landry, PhD Sources (25)
- [1] Barger LK, Rajaratnam SM, Wang W, et al. Common sleep disorders increase risk of motor vehicle crashes and adverse health outcomes in firefighters. Journal of Clinical Sleep Medicine. 2015;11(3):233–240. (Screening questionnaires and self-report; cross-sectional.) Barger et al., 2015 (PubMed)
- [2] Rajaratnam SM, Barger LK, Lockley SW, et al. Sleep disorders, health, and safety in police officers. JAMA. 2011;306(23):2567–2578. (Screening questionnaires and self-report.) Rajaratnam et al., 2011 (PubMed)
- [3] Patterson PD, Weaver MD, Frank RC, et al. Association between poor sleep, fatigue, and safety outcomes in emergency medical services providers. Prehospital Emergency Care. 2012;16(1):86–97. (Convenience sample; the authors describe the evidence as preliminary.) Patterson et al., 2012 (PubMed)
- [4] Huang G, Lee TY, Banda KJ, et al. Prevalence of sleep disorders among first responders for medical emergencies: a meta-analysis. Journal of Global Health. 2022;12:04092. Huang et al., 2022 (PubMed)
- [5] Angehrn A, Teale Sapach MJN, Ricciardelli R, et al. Sleep quality and mental disorder symptoms among Canadian public safety personnel. International Journal of Environmental Research and Public Health. 2020;17(8):2708. (Online, self-selected survey.) Angehrn et al., 2020 (PubMed)
- [6] Sullivan JP, O'Brien CS, Barger LK, Rajaratnam SM, Czeisler CA, Lockley SW. Randomized, prospective study of the impact of a sleep health program on firefighter injury and disability. Sleep. 2017;40(1):zsw001. Sullivan et al., 2017 (PubMed)
- [7] Patterson PD, Higgins JS, Van Dongen HPA, et al. Evidence-based guidelines for fatigue risk management in emergency medical services. Prehospital Emergency Care. 2018;22(sup1):89–101. Patterson et al., 2018a (PubMed)
- [8] Patterson PD, Runyon MS, Higgins JS, et al. Shorter versus longer shift durations to mitigate fatigue and fatigue-related risks in emergency medical services personnel and related shift workers: a systematic review. Prehospital Emergency Care. 2018;22(sup1):28–36. (Evidence quality low or very low.) Patterson et al., 2018b (PubMed)
- [9] Violanti JM, Fekedulegn D, Andrew ME, et al. Shift work and the incidence of injury among police officers. American Journal of Industrial Medicine. 2012;55(3):217–227. (One mid-sized urban department.) Violanti et al., 2012 (PubMed)
- [10] Riedy SM, Dawson D, Vila B. U.S. police rosters: fatigue and public complaints. Sleep. 2019;42(3):zsy231. (Fatigue estimated with a biomathematical model.) Riedy et al., 2019 (PubMed)
- [11] Waggoner LB, Grant DA, Van Dongen HP, Belenky G, Vila B. A combined field and laboratory design for assessing the impact of night shift work on police officer operational performance. Sleep. 2012;35(11):1575–1577. (29 officers.) Waggoner et al., 2012 (PubMed)
- [12] Williamson AM, Feyer AM. Moderate sleep deprivation produces impairments in cognitive and motor performance equivalent to legally prescribed levels of alcohol intoxication. Occupational and Environmental Medicine. 2000;57(10):649–655. Williamson & Feyer, 2000 (journal)
- [13] Dawson D, Reid K. Fatigue, alcohol and performance impairment. Nature. 1997;388(6639):235. Dawson & Reid, 1997 (journal)
- [14] Arnedt JT, Wilde GJ, Munt PW, MacLean AW. How do prolonged wakefulness and alcohol compare in the decrements they produce on a simulated driving task? Accident Analysis & Prevention. 2001;33(3):337–344. Arnedt et al., 2001 (PubMed)
- [15] Stepan ME, Wilckens KA, Hostler D, Wallace ML, Franzen PL. Physical exertion partially mitigates task-switching deficits from sleep loss: implications for firefighters. Journal of Occupational and Environmental Medicine. 2022;64(10):e622–e628. (24 men, laboratory study.) Stepan et al., 2022 (PubMed)
- [16] Vincent GE, Ferguson S, Larsen B, Ridgers ND, Snow R, Aisbett B. Adding sleep restriction to the equation: impact on wildland firefighters' work performance and physiology in hot conditions. International Archives of Occupational and Environmental Health. 2018;91(5):601–611. (31 firefighters, simulated conditions.) Vincent et al., 2018 (PubMed)
- [17] Van Dongen HP, Maislin G, Mullington JM, Dinges DF. The cumulative cost of additional wakefulness: dose-response effects on neurobehavioral functions and sleep physiology from chronic sleep restriction and total sleep deprivation. Sleep. 2003;26(2):117–126. Van Dongen et al., 2003 (PubMed)
- [18] Blatter K, Cajochen C. Circadian rhythms in cognitive performance: methodological constraints, protocols, theoretical underpinnings. Physiology & Behavior. 2007;90(2-3):196–208. Blatter & Cajochen, 2007 (journal)
- [19] Klein R, Armitage R. Rhythms in human performance: 1½-hour oscillations in cognitive style. Science. 1979;204(4399):1326–1328. (Small early study; 60–100-minute cycles.) Klein & Armitage, 1979 (journal)
- [20] Wolkow AP, Barger LK, O'Brien CS, et al. Associations between sleep disturbances, mental health outcomes and burnout in firefighters, and the mediating role of sleep during overnight work: a cross-sectional study. Journal of Sleep Research. 2019;28(6):e12869. Wolkow et al., 2019 (PubMed)
- [21] Yoo SS, Gujar N, Hu P, Jolesz FA, Walker MP. The human emotional brain without sleep: a prefrontal amygdala disconnect. Current Biology. 2007;17(20):R877–R878. (Small study; total sleep deprivation for one night.) Yoo et al., 2007 (journal)
- [22] Folkard S. Black times: temporal determinants of transport safety. Accident Analysis & Prevention. 1997;29(4):417–430. Folkard, 1997 (PubMed)
- [23] Horne JA, Reyner LA. Sleep related vehicle accidents. BMJ. 1995;310(6979):565–567. Horne & Reyner, 1995 (PubMed)
- [24] CSA Group. CSA Z1615:22, First responder fatigue risk management system (National Standard of Canada). 2022. CSA Z1615:22, 2022 (CSA Group)
- [25] Watson NF, Badr MS, Belenky G, et al. Recommended amount of sleep for a healthy adult: a joint consensus statement of the American Academy of Sleep Medicine and Sleep Research Society. Journal of Clinical Sleep Medicine. 2015;11(6):591–592. Watson et al., 2015 (journal)


